Thank you for choosing Rose Medical Clinic for your dental care. We appreciate the opportunity to serve you. After a thorough examination, we would like to share the findings & recommenda- tions for your dental health.
Medical plan:
Visit details:
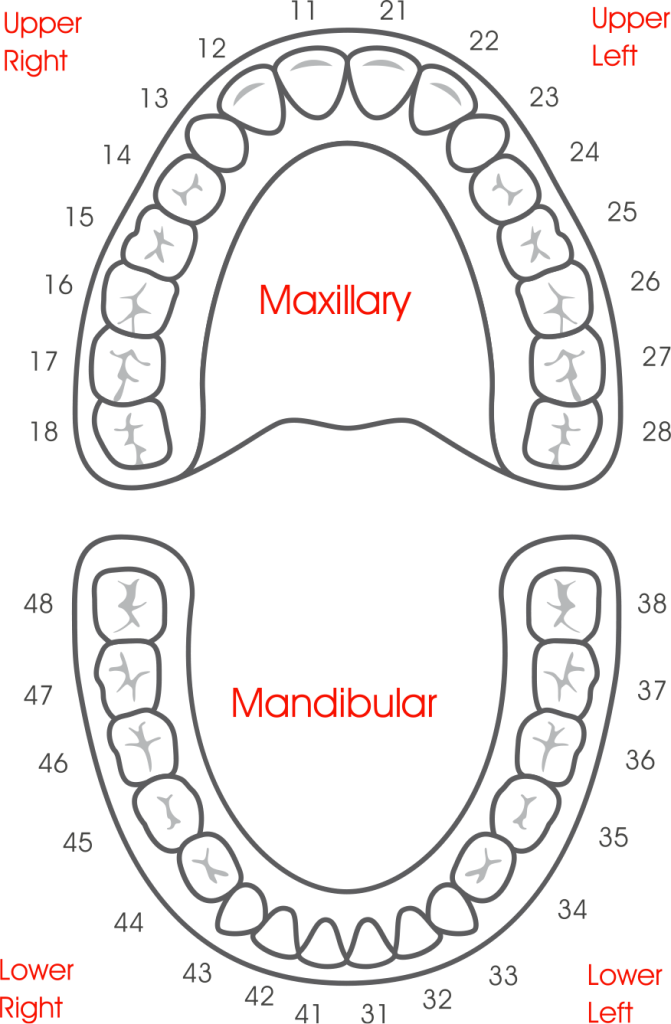
Dental report
The Cost
1st visit cost:
Treatment Type
Brand
Quantity
Cost per one
Total
Important Payment and Appointment Information
Please take note of the following details:
Payment: Cash only. Other methods include a 20% tax.
Appointment Fee: Pay the total amount during treatment appointment after consultation.
Free Panoramic X-Ray: Includes exam and X-ray by our specialist. Additional costs may apply for sinus elevations or root canals.